
Immunophenotypic Characterisation of Mixed Phenotype Acute Leukemia: A Review of Published Series
DOI:
https://doi.org/10.5281/zenodo.22227758Keywords:
Mixed Phenotype Acute Leukaemia, Immunophenotyping, Myeloperoxidase, Lineage Assignment, Flow CytometryAbstract
Mixed phenotype acute leukaemia is defined by antigen expression thresholds expressed relative to normal cells, and the resulting label determines whether a patient receives lymphoblastic-directed or myeloid-directed therapy. Since lymphoblastic-directed treatment produces better outcomes, a relative flow cytometric measurement is doing more clinical work than its reproducibility comfortably supports. Objectives: To review the published evidence on immunophenotypic characterisation of mixed phenotype acute leukaemia: which markers define each lineage and at what thresholds, how the lineage combinations distribute, how immunophenotype relates to morphology and cytogenetics, and how the assignment influences treatment and outcome.
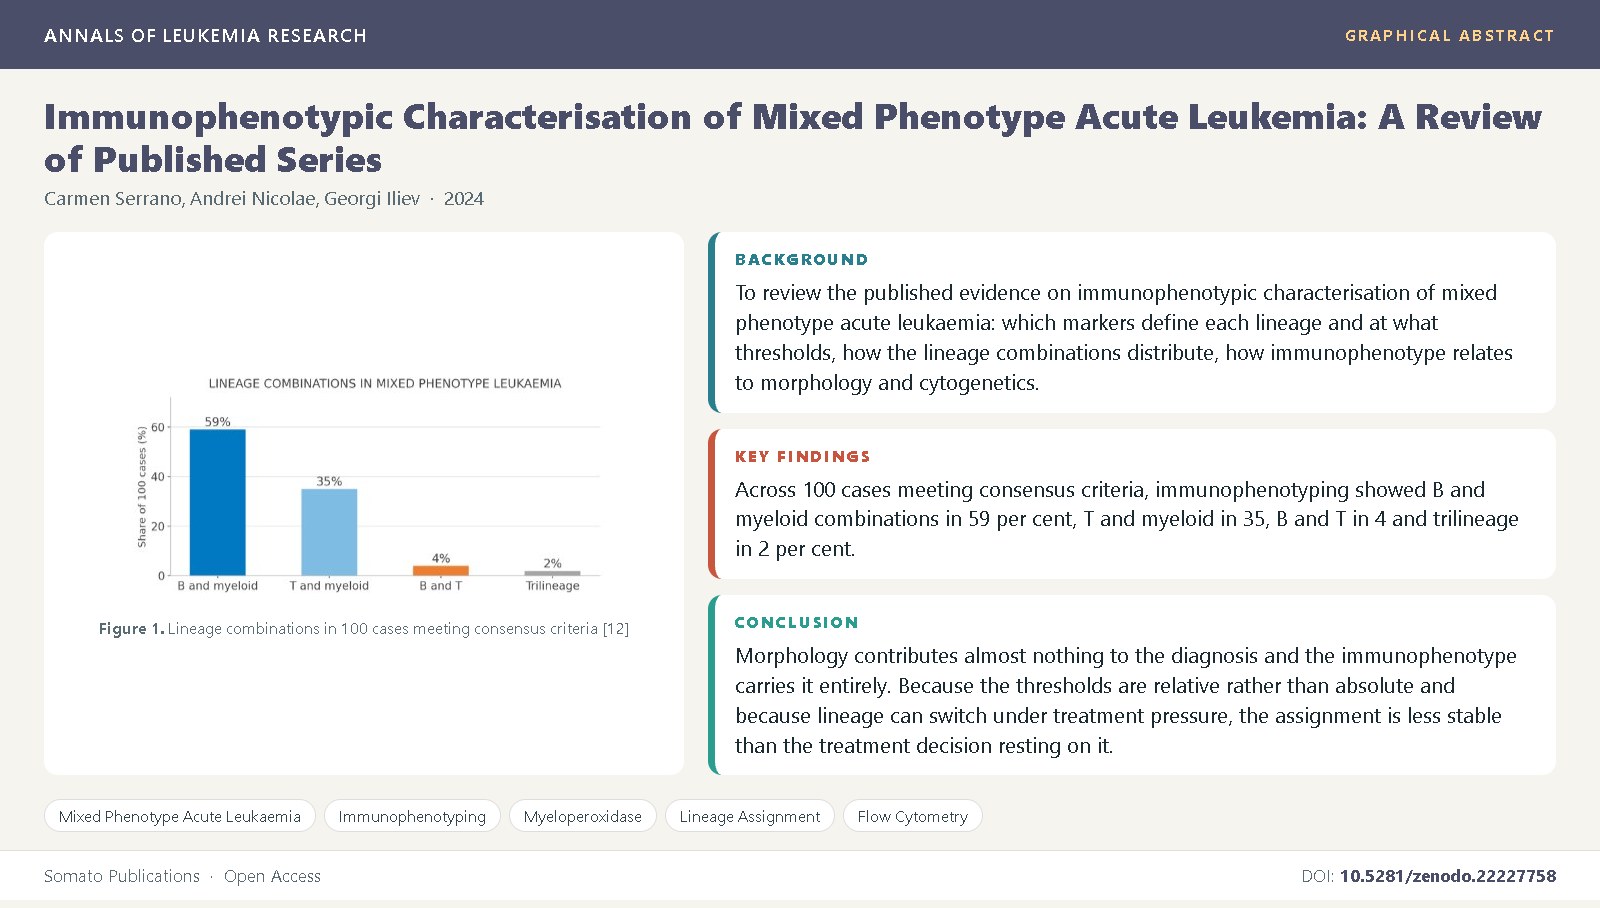
Material and Methods: Narrative review of clinicopathological series, classification documents, diagnostic reviews and case reports indexed in PubMed and the major haematology and pathology journals. Studies were eligible if they reported immunophenotypic features, diagnostic criteria or outcomes in a defined mixed phenotype acute leukaemia population. No new patient data were generated and no patients were recruited; every estimate quoted is one published by the original investigators. Results: Across 100 cases meeting consensus criteria, immunophenotyping showed B and myeloid combinations in 59 per cent, T and myeloid in 35, B and T in 4 and trilineage in 2 per cent. Morphology was consistent with lymphoblastic leukaemia in 43 per cent, myeloid in 42 and inconclusive in 15, and there was no correlation between age, morphology, immunophenotype or cytogenetics. Cytogenetic findings were complex in 32 per cent, otherwise aberrant in 27, t(9;22) in 20, normal in 13 and 11q23 rearranged in 8 per cent. In a separate series of 52 patients, 69.2 per cent received lymphoblastic-directed and 30.8 per cent myeloid-directed regimens, complete remission was achieved in 76.9 per cent, and lymphoblastic-directed treatment, paediatric age and biphenotypic blast type were each associated with higher remission rates and better overall survival.Conclusion: Morphology contributes almost nothing to the diagnosis and the immunophenotype carries it entirely. Because the thresholds are relative rather than absolute and because lineage can switch under treatment pressure, the assignment is less stable than the treatment decision resting on it. Abbreviations: MPAL – Mixed Phenotype Acute Leukaemia, ALAL – Acute Leukaemia of Ambiguous Lineage, BAL – Biphenotypic Acute Leukaemia, ALL – Acute Lymphoblastic Leukaemia, AML – Acute Myeloid Leukaemia, MPO – Myeloperoxidase, cCD3 – Cytoplasmic CD3, sCD3 – Surface CD3, EGIL –
European Group for the Immunological Characterization of Leukemias, WHO – World Health Organization, ICC – International Consensus Classification, NSE – Nonspecific Esterase, My+ ALL – Myeloid Antigen-Positive ALL, CR – Complete Remission.
References
Weinberg, OK., Arber, DA. (2010) Mixed-phenotype acute leukemia: historical overview and a new definition. Leukemia, 24(11): 1844-1851.
Vardiman, JW., Thiele, J., Arber, DA., Brunning, RD., Borowitz, MJ., Porwit, A., et al. (2009) The 2008 revision of the World Health Organization classification of myeloid neoplasms and acute leukemia: rationale and important changes. Blood, 114(5): 937-951.
Sherban, A., Wolach, O. (2023) Acute leukemia of ambiguous lineage. Haematologica, 108(9): 2275-2286.
Wolach, O., Stone, RM. (2015) How I treat mixed-phenotype acute leukemia. Blood, 125(16): 2477-2485.
Charles, NJ., Boyer, DF. (2017) Mixed-phenotype acute leukemia: diagnostic criteria and pitfalls. Arch Pathol Lab Med, 141(11): 1462-1468.
Weinberg, OK., Seetharam, M., Ren, L., Alizadeh, A., Arber, DA. (2014) Mixed phenotype acute leukemia: a study of 61 cases using World Health Organization and European Group for the Immunological Classification of Leukaemias criteria. Am J Clin Pathol, 142(6): 803-808.
Rimando, J., Slade, M., Wallace, N., DiPersio, JF., Westervelt, P., Uy, GL. (2018) Biphenotypic acute leukemia versus myeloid antigen-positive ALL: clinical relevance of WHO criteria for mixed phenotype acute leukemia. Case Rep Hematol, 2018: 8032679.
Gerr, H., Zimmermann, M., Schrappe, M., Dworzak, M., Ludwig, WD., Bradtke, J., et al. (2010) Acute leukaemias of ambiguous lineage in children: characterization, prognosis and therapy recommendations. Br J Haematol, 149(1): 84-92.
Zhang, Y., Wang, L., Li, J., Chen, H., Liu, X., Sun, M., et al. (2026) Immunophenotypically defined mixed-phenotype acute leukemias: a clinicopathologic analysis of 52 cases. eJHaem, 7(1): e70196.
Rubnitz, JE., Onciu, M., Pounds, S., Shurtleff, S., Cao, X., Raimondi, SC., et al. (2009) Acute mixed lineage leukemia in children: the experience of St Jude Children’s Research Hospital. Blood, 113(21): 5083-5089.
Yan, L., Ping, N., Zhu, M., Sun, A., Xue, Y., Ruan, C., et al. (2012) Clinical, immunophenotypic, cytogenetic, and molecular genetic features in 117 adult patients with mixed-phenotype acute leukemia defined by WHO-2008 classification. Haematologica, 97(11): 1708-1712.
Matutes, E., Pickl, WF., Van’t Veer, M., Morilla, R., Swansbury, J., Strobl, H., Attarbaschi, A., Hopfinger, G., Ashley, S., Bene, MC., Porwit, A., Orfao, A., Lemez, P., Schabath, R., Ludwig, WD. (2011) Mixed-phenotype acute leukemia: clinical and laboratory features and outcome in 100 patients defined according to the WHO 2008 classification. Blood, 117(11): 3163-3171.
Hrusak, O., de Haas, V., Stancikova, J., Vakrmanova, B., Janotova, I., Mejstrikova, E., et al. (2018) International cooperative study identifies treatment strategy in childhood ambiguous lineage leukemia. Blood, 132(3): 264-276.
Al-Seraihy, AS., Owaidah, TM., Ayas, M., El-Solh, H., Al-Mahr, M., Al-Ahmari, A., Belgaumi, AF. (2009) Clinical characteristics and outcome of children with biphenotypic acute leukemia. Haematologica, 94(12): 1682-1690.
Killick, S., Matutes, E., Powles, RL., Hamblin, M., Swansbury, J., Treleaven, JG., et al. (1999) Outcome of biphenotypic acute leukemia. Haematologica, 84(8): 699-706.
Alexander, TB., Gu, Z., Iacobucci, I., Dickerson, K., Choi, JK., Xu, B., et al. (2018) The genetic basis and cell of origin of mixed phenotype acute leukaemia. Nature, 562(7727): 373-379.
Takahashi, K., Wang, F., Morita, K., Yan, Y., Hu, P., Zhao, P., et al. (2018) Integrative genomic analysis of adult mixed phenotype acute leukemia delineates lineage associated molecular subtypes. Nat Commun, 9(1): 2670.
Xiao, W., Bharadwaj, M., Levine, M., Farnhoud, N., Pastore, F., Getta, BM., et al. (2018) PHF6 and DNMT3A mutations are enriched in distinct subgroups of mixed phenotype acute leukemia with T-lineage differentiation. Blood Adv, 2(23): 3526-3539.
Duong, VH., Begna, KH., Kashanian, S., Sweet, K., Wang, ES., Caldwell, A., et al. (2020) Favorable outcomes of acute leukemias of ambiguous lineage treated with hyperCVAD: a multi-center retrospective study. Ann Hematol, 99(9): 2119-2124.
Liu, Y., Zhang, X., Chen, W., Li, H., Wang, Q., Zhao, J., et al. (2022) Diagnostic challenge in mixed phenotype acute leukemia with T/megakaryocyte or T/myeloid lineages accompanied by t(3;3). Front Oncol, 12: 972062.
Manola, KN. (2013) Cytogenetics of pediatric acute myeloid leukemia. Eur J Haematol, 90(4): 279-290.
Kantarjian, H., Kadia, T., DiNardo, C., Daver, N., Borthakur, G., Jabbour, E., et al. (2021) Acute myeloid leukemia: current progress and future directions. Blood Cancer J, 11: 41.
Roberts, KG. (2018) Genetics and prognosis of ALL in children vs adults. Hematology Am Soc Hematol Educ Program, 2018: 137-145.
Döhner, H., Wei, AH., Appelbaum, FR., Craddock, C., DiNardo, CD., Dombret, H., et al. (2022) Diagnosis and management of AML in adults: 2022 recommendations from an international expert panel on behalf of the ELN. Blood, 140(12): 1345-1377.
Kayser, S., Levis, MJ. (2021) Updates on targeted therapies for acute myeloid leukaemia. Br J Haematol, 196(2): 316-328.





