
Central Nervous System Involvement at Diagnosis in Infants with Acute Lymphoblastic Leukemia (ALL): Incidence and Outcome
DOI:
https://doi.org/10.5281/zenodo.22213650Keywords:
Infant Leukaemia, Acute Lymphoblastic Leukaemia, Central Nervous System, KMT2A Rearrangement, InterfantAbstract
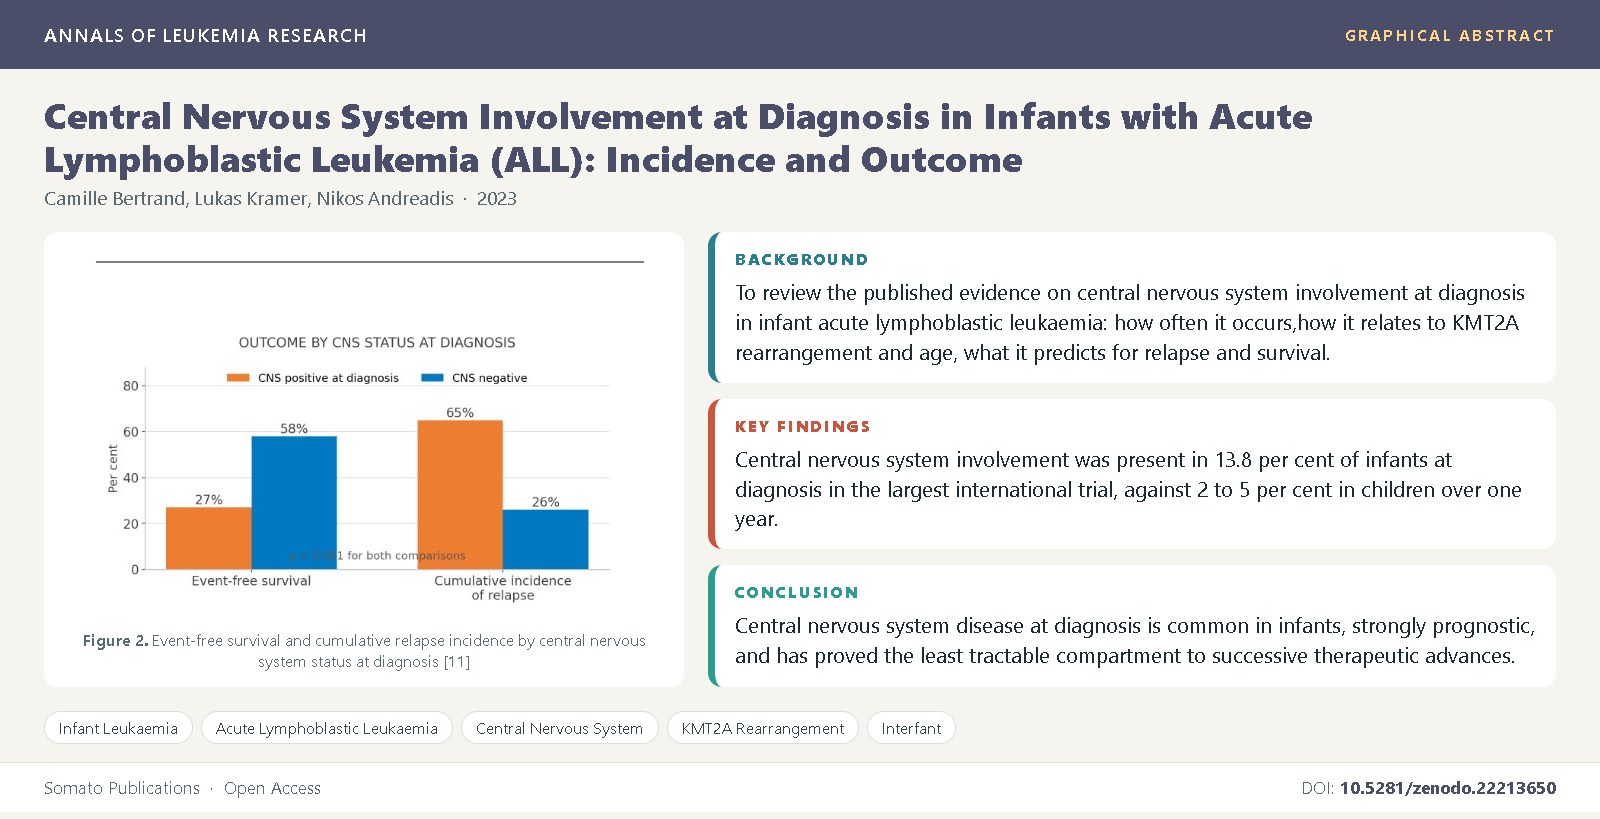
Infants under one year with acute lymphoblastic leukaemia present with central nervous system disease three to five times more often than older children, and it identifies a group whose event-free survival is roughly half that of their central nervous system-negative peers. The newest and most effective therapy for these infants may not reach that compartment at all. Objectives: To review the published evidence on central nervous system involvement at diagnosis in infant acute lymphoblastic leukaemia: how often it occurs,
how it relates to KMT2A rearrangement and age, what it predicts for relapse and survival, and how the compartment has responded to successive treatment strategies. Material and Methods: Narrative review of international cooperative group trials, registry analyses and correlative studies indexed in PubMed and the major haematology and oncology journals. Studies were eligible if they reported the frequency or outcome of central nervous system disease in a defined infant leukaemia population, or the effect of a treatment strategy on central nervous system relapse. No new patient data were generated and no patients were recruited; every estimate quoted is one published by the original investigators. Results: Central nervous system involvement was present in 13.8 per cent of infants at diagnosis in the largest international trial, against 2 to 5 per cent in children over one year. Among 139 infants with recorded status, 28 of 50 with central nervous system disease relapsed, giving event-free survival of 0.27 and cumulative relapse incidence of 0.65, against 21 relapses among 89 without involvement, event-free survival 0.58 and relapse incidence 0.26 (p < 0.001 for both). Of 213 relapses occurring after first remission in 442 patients, 24 per cent involved the central nervous system, comprising 11 per cent isolated and 13 per cent
combined marrow and central nervous system disease. Adding one course of a CD19-directed bispecific antibody to the same chemotherapy backbone raised two-year disease-free survival from 49.4 to 81.6 per cent, yet every relapse that occurred involved the central nervous system. Conclusion: Central nervous system disease at diagnosis is common in infants, strongly prognostic, and has proved the least tractable compartment to successive therapeutic advances. That the most effective new agent leaves relapses concentrated there is an argument for intensifying intrathecal rather than systemic therapy alongside it. Abbreviations: ALL – Acute Lymphoblastic Leukaemia, CNS – Central Nervous System, KMT2A-r – KMT2A-Rearranged, KMT2A-g – KMT2A-Germline,
EFS – Event-Free Survival, DFS – Disease-Free Survival, OS – Overall Survival, CIR – Cumulative Incidence of Relapse, CR1 – FirstComplete Remission, MRD – Minimal Residual Disease, HSCT – Haematopoietic Stem Cell Transplantation, WBC – White Blood Cell Count.
References
Sanvisens, A., Bueno, C., Calvete, O., Solé, F., Marcos-Gragera, R., Solans, M. (2025) Prenatal and perinatal factors associated with infant acute lymphoblastic leukaemia: a scoping review. Cancers, 17(3): 370.
Kulczycka, M., Derlatka, K., Tasior, J., Sygacz, M., Lejman, M., Zawitkowska, J. (2024) Infant acute lymphoblastic leukemia: new therapeutic opportunities. Int J Mol Sci, 25(7): 3721.
Pieters, R., Schrappe, M., De Lorenzo, P., Hann, I., De Rossi, G., Felice, M., et al. (2007) A treatment protocol for infants younger than 1 year with acute lymphoblastic leukaemia (Interfant-99): an observational study and a multicentre randomised trial. Lancet, 370(9583): 240-250.
Pieters, R., De Lorenzo, P., Ancliffe, P., Aversa, LA., Brethon, B., Biondi, A., et al. (2019) Outcome of infants younger than 1 year with acute lymphoblastic leukemia treated with the Interfant-06 protocol: results from an international phase III randomized study. J Clin Oncol, 37(25): 2246-2256.
Boissel, N., Baruchel, A. (2018) Acute lymphoblastic leukemia in adolescent and young adults: treat as adults or as children? Blood, 132(4): 351-361.
Roberts, KG. (2018) Genetics and prognosis of ALL in children vs adults. Hematology Am Soc Hematol Educ Program, 2018: 137-145.
Nagayama, J., Tomizawa, D., Koh, K., Nagatoshi, Y., Hotta, N., Kishimoto, T., et al. (2006) Infants with acute lymphoblastic leukemia and a germline MLL gene are highly curable with use of chemotherapy alone: results from the Japan Infant Leukemia Study Group. Blood, 107(12): 4663-4665.
van der Sluis, IM., de Lorenzo, P., Kotecha, RS., Attarbaschi, A., Escherich, G., Nysom, K., et al. (2023) Blinatumomab added to chemotherapy in infant lymphoblastic leukemia. N Engl J Med, 388(17): 1572-1581.
Robinson, BW., Kairalla, JA., Devidas, M., Heerema, NA., Carroll, AJ., et al. (2023) KMT2A partner genes in infant acute lymphoblastic leukemia have prognostic significance and correlate with age, white blood cell count, sex, and central nervous system involvement: a Children’s Oncology Group P9407 trial study. Haematologica, 108(10): 2865-2871.
Stutterheim, J., Stam, RW., van der Sluis, IM., et al. (2025) KMT2A-rearranged acute lymphoblastic leukemia in infants: current progress and challenges. Haematologica.
Barrett, N., Gruber, TA., Miyamura, T., Duguid, A., Stutterheim, J. (2025) Infant acute lymphoblastic leukaemia: progress from worldwide clinical efforts. Br J Haematol, 207(6): 2246-2260.
Pichler, H., Reismuller, B., Steiner, M., Dworzak, MN., Palfi, M., et al. (2013) The inferior prognosis of adolescents with acute lymphoblastic leukaemia (ALL) is caused by a higher rate of treatment-related mortality and not an increased relapse rate. Br J Haematol, 161(4): 556-565.
Lazarus, HM., Richards, SM., Chopra, R., Litzow, MR., Burnett, AK., et al. (2006) Central nervous system involvement in adult acute lymphoblastic leukemia at diagnosis: results from the international ALL trial MRC UKALL XII/ECOG E2993. Blood, 108(2): 465-472.
Hilden, JM., Dinndorf, PA., Meerbaum, SO., Sather, H., Villaluna, D., Heerema, NA., et al. (2006) Analysis of prognostic factors of acute lymphoblastic leukemia in infants: report on CCG 1953 from the Children’s Oncology Group. Blood, 108(2): 441-451.
Mann, G., Attarbaschi, A., Schrappe, M., De Lorenzo, P., Peters, C., Hann, I., et al. (2010) Improved outcome with hematopoietic stem cell transplantation in a poor prognostic subgroup of infants with mixed-lineage-leukemia (MLL)-rearranged acute lymphoblastic leukemia: results from the Interfant-99 study. Blood, 116(15): 2644-2650.
Stutterheim, J., de Lorenzo, P., van der Sluis, IM., Alten, J., Ancliffe, P., Attarbaschi, A., et al. (2022) Minimal residual disease and outcome characteristics in infant KMT2A-germline acute lymphoblastic leukaemia treated on the Interfant-06 protocol. Eur J Cancer, 160: 72-79.
Sidaway, P. (2023) Blinatumomab improves outcomes in infant ALL. Nat Rev Clin Oncol, 20(7): 426.
Paul, S., Kantarjian, H., Jabbour, EJ. (2016) Adult acute lymphoblastic leukemia. Mayo Clin Proc, 91(11): 1645-1666.
Stutterheim, J., van der Sluis, IM., de Lorenzo, P., Alten, J., Ancliffe, P., Attarbaschi, A., et al. (2021) Clinical implications of minimal residual disease detection in infants with KMT2A-rearranged acute lymphoblastic leukemia treated on the Interfant-06 protocol. J Clin Oncol, 39(6): 652-662.
Dreyer, Z., Hilden, J., Jones, T., Devidas, M., Winick, NJ., Willman, CL., et al. (2015) Intensified chemotherapy without SCT in infant ALL: results from COG P9407 (cohort 3). Pediatr Blood Cancer, 62(3): 419-426.
Brown, PA., Kairalla, JA., Hilden, JM., Dreyer, ZE., Carroll, AJ., et al. (2021) FLT3 inhibitor lestaurtinib plus chemotherapy for newly diagnosed KMT2A-rearranged infant acute lymphoblastic leukemia: Children’s Oncology Group trial AALL0631. Leukemia, 35(5): 1279-1290.
Guest, EM., Kairalla, JA., Hilden, JM., Dreyer, ZAE., Carroll, AJ., Heerema, NA., et al. (2022) Outstanding outcomes in infants with KMT2A-germline acute lymphoblastic leukemia treated with chemotherapy alone: results of the Children’s Oncology Group AALL0631 trial. Haematologica, 107(5): 1205-1208.
Fazio, G., Bardini, M., de Lorenzo, P., Grioni, A., Quadri, M., Pedace, L., et al. (2020) Recurrent genetic fusions redefine MLL-germline acute lymphoblastic leukemia in infants. Blood, 137(14): 1980-1984.
Mironova, D., Saraswati, CM., Downie, P., Lai, CY., Cook, E., Carruthers, V., et al. (2023) Late effects in survivors of infant acute lymphoblastic leukaemia: a study of the Australian and New Zealand Children’s Haematology/Oncology Group. Blood Cancer J, 13: 148.
Driessen, EMC., de Lorenzo, P., Campbell, M., Felice, M., Ferster, A., et al. (2016) Outcome of relapsed infant acute lymphoblastic leukemia treated on the Interfant-99 protocol. Leukemia, 30(5): 1184-1187.





