
Early Response Assessment by Minimal Residual Disease in Adolescents with T-Cell Acute Lymphoblastic Leukemia (T-ALL)
DOI:
https://doi.org/10.5281/zenodo.22213672Keywords:
T-Cell Acute Lymphoblastic Leukaemia, Minimal Residual Disease, Adolescents, Risk Stratification, Treatment ResponseAbstract
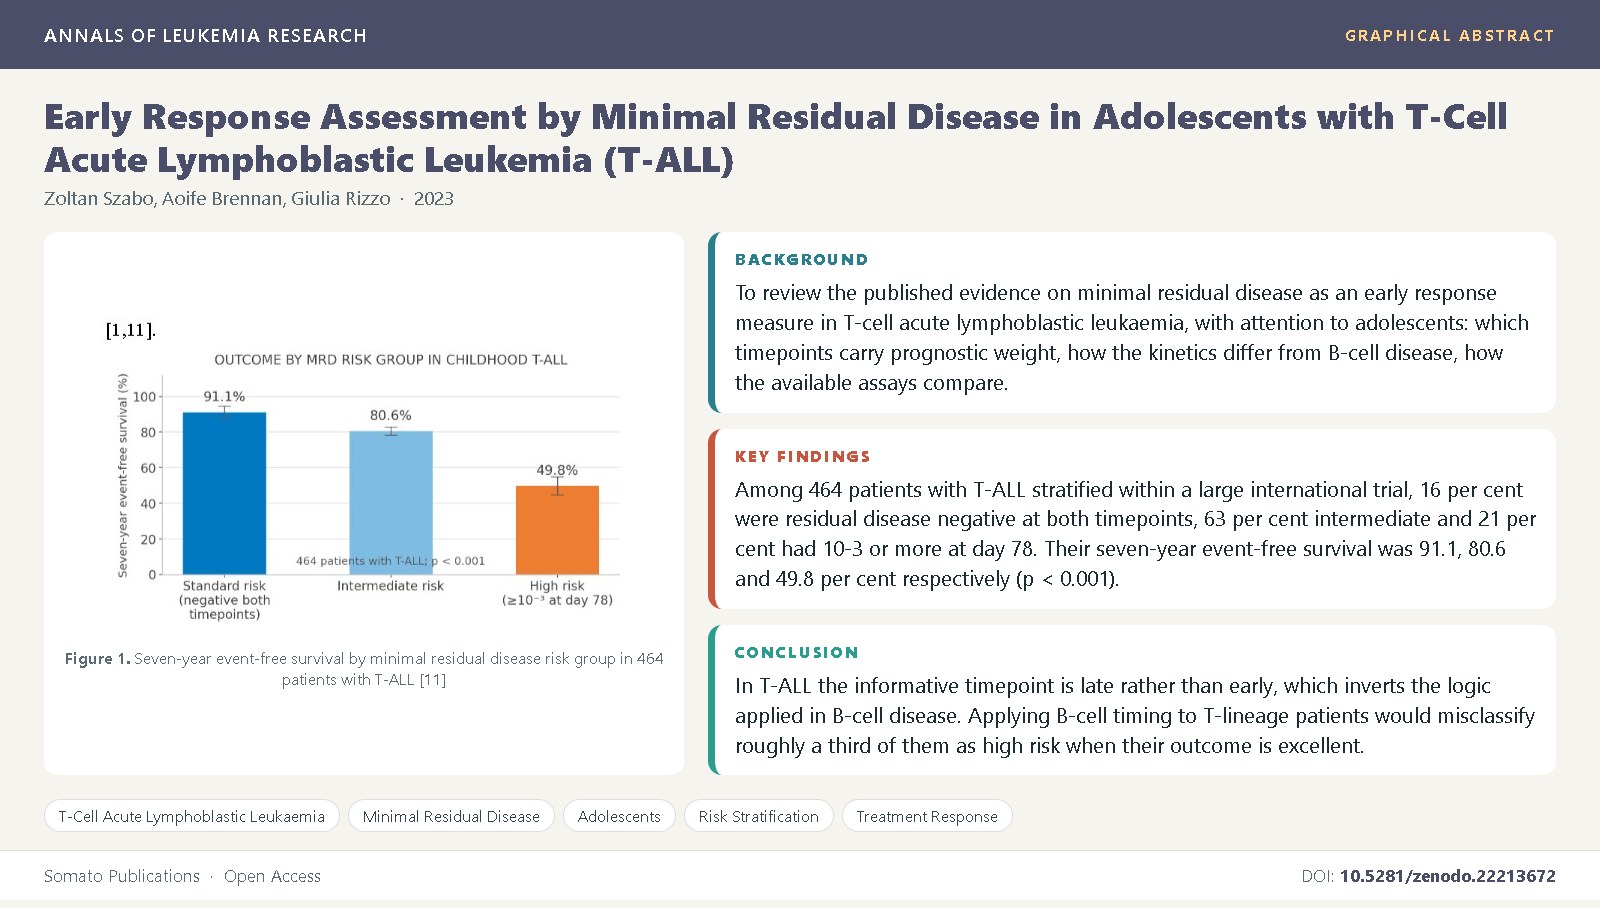
Minimal residual disease has displaced almost every other prognostic variable in acute lymphoblastic leukaemia, but the timing that works for B-cell disease does not transfer to T-lineage disease. T-cell blasts clear more slowly, and an early measurement that would condemn a B-cell patient turns out to carry no information at all in T-ALL provided the later measurement is clear. Objectives: To review the published evidence on minimal residual disease as an early response measure in T-cell acute lymphoblastic leukaemia, with attention to adolescents: which timepoints carry prognostic weight, how the kinetics differ from B-cell disease, how the available assays compare, and what the measurement has been used to change. Material and Methods: Narrative review of cooperative group trials, methodological comparisons and response-adapted randomised studies indexed in PubMed and the major haematology journals. Studies were eligible if they reported the prognostic value of minimal residual disease in a defined acute lymphoblastic
leukaemia population, compared assay platforms, or tested treatment modification on the basis of residual disease. No new patient data were generated and no patients were recruited; every estimate quoted is one published by the original investigators.
Results: Among 464 patients with T-ALL stratified within a large international trial, 16 per cent were residual disease negative at both timepoints, 63 per cent intermediate and 21 per cent had 10-3 or more at day 78. Their seven-year event-free survival was 91.1, 80.6 and 49.8 per cent respectively (p < 0.001). Only 16 per cent of T-ALL patients cleared at the first timepoint against 42 per cent of 3,184 patients with B-cell precursor disease. Critically, the 32 per cent of T-ALL patients who became negative only at the second timepoint did equally well, indicating that early residual disease level is irrelevant provided the later measurement is clear. Residual disease at or above 10-3 at day 78 was the single most important predictor of relapse. At day 29, hazard ratios for relapse were 3.55 by flow cytometry and 5.6 by polymerase chain reaction. Conclusion: In T-ALL the informative timepoint is late rather than early, which inverts the logic applied in B-cell disease. Applying B-cell timing to T-lineage patients would misclassify roughly a third of them as high risk when their outcome is excellent. Abbreviations: ALL – Acute Lymphoblastic Leukaemia, T-ALL – T-Cell Acute Lymphoblastic Leukaemia, BCP-ALL – B-Cell Precursor ALL, MRD – Minimal Residual Disease, TP1 – Time Point 1, TP2 – Time Point 2, FCM – Flow Cytometry, RQ-PCR – Real-Time Quantitative Polymerase Chain Reaction, Ig/TCR – Immunoglobulin and T-Cell Receptor, ETP – Early T-Cell Precursor, EFS – Event-Free Survival, HSCT – Haematopoietic Stem Cell Transplantation, AYA – Adolescent and Young Adult.
References
Marks, DI., Rowntree, C. (2017) Management of adults with T-cell lymphoblastic leukemia. Blood, 129(9): 1134-1142.
Roberts, KG. (2018) Genetics and prognosis of ALL in children vs adults. Hematology Am Soc Hematol Educ Program, 2018: 137-145.
Paul, S., Kantarjian, H., Jabbour, EJ. (2016) Adult acute lymphoblastic leukemia. Mayo Clin Proc, 91(11): 1645-1666.
Curran, E., Stock, W. (2015) How I treat acute lymphoblastic leukemia in older adolescents and young adults. Blood, 125(24): 3702-3710.
Stock, W., Luger, SM., Advani, AS., Yin, J., Harvey, RC., Mullighan, CG., et al. (2019) A pediatric regimen for older adolescents and young adults with acute lymphoblastic leukemia: results of CALGB 10403. Blood, 133(14): 1548-1559.
Boissel, N., Baruchel, A. (2018) Acute lymphoblastic leukemia in adolescent and young adults: treat as adults or as children? Blood, 132(4): 351-361.
Huguet, F., Leguay, T., Raffoux, E., Thomas, X., Beldjord, K., Delabesse, E., et al. (2009) Pediatric-inspired therapy in adults with Philadelphia chromosome-negative acute lymphoblastic leukemia: the GRAALL-2003 study. J Clin Oncol, 27(6): 911-918.
Pichler, H., Reismuller, B., Steiner, M., Dworzak, MN., Palfi, M., et al. (2013) The inferior prognosis of adolescents with acute lymphoblastic leukaemia (ALL) is caused by a higher rate of treatment-related mortality and not an increased relapse rate. Br J Haematol, 161(4): 556-565.
Flohr, T., Schrauder, A., Cazzaniga, G., Panzer-Grümayer, R., van der Velden, V., et al. (2008) Minimal residual disease-directed risk stratification using real-time quantitative PCR analysis of immunoglobulin and T-cell receptor gene rearrangements in the international multicenter trial AIEOP-BFM ALL 2000 for childhood acute lymphoblastic leukemia. Leukemia, 22(4): 771-782.
Conter, V., Bartram, CR., Valsecchi, MG., Schrauder, A., Panzer-Grümayer, R., Möricke, A., et al. (2010) Molecular response to treatment redefines all prognostic factors in children and adolescents with B-cell precursor acute lymphoblastic leukemia: results in 3184 patients of the AIEOP-BFM ALL 2000 study. Blood, 115(16): 3206-3214.
Schrappe, M., Valsecchi, MG., Bartram, CR., Schrauder, A., Panzer-Grümayer, R., Möricke, A., et al. (2011) Late MRD response determines relapse risk overall and in subsets of childhood T-cell ALL: results of the AIEOP-BFM-ALL 2000 study. Blood, 118(8): 2077-2084.
Cario, G., Valsecchi, MG., Conter, V., et al. (2025) Results in pediatric T-ALL patients treated in trial AIEOP-BFM ALL 2009: prognostic factors in the context of modern risk-adapted therapy. Hemasphere, 9: e70206.
Modvig, S., Madsen, HO., Siitonen, SM., Rosthoj, S., Tierens, A., et al. (2019) Minimal residual disease quantification by flow cytometry provides reliable risk stratification in T-cell acute lymphoblastic leukemia. Leukemia, 33(6): 1324-1336.
Vora, A., Goulden, N., Wade, R., Mitchell, C., Hancock, J., et al. (2013) Treatment reduction for children and young adults with low-risk acute lymphoblastic leukaemia defined by minimal residual disease (UKALL 2003): a randomised controlled trial. Lancet Oncol, 14(3): 199-209.
Vora, A., Goulden, N., Mitchell, C., Hancock, J., Hough, R., Rowntree, C., et al. (2014) Augmented post-remission therapy for a minimal residual disease-defined high-risk subgroup of children and young people with clinical standard-risk and intermediate-risk acute lymphoblastic leukaemia (UKALL 2003): a randomised controlled trial. Lancet Oncol, 15(8): 809-818.
Pieters, R., de Groot-Kruseman, H., Van der Velden, V., Fiocco, M., van den Berg, H., et al. (2016) Successful therapy reduction and intensification for childhood acute lymphoblastic leukemia based on minimal residual disease monitoring: study ALL10 from the Dutch Childhood Oncology Group. J Clin Oncol, 34(22): 2591-2601.
Gupta, S., Devidas, M., Loh, ML., Raetz, EA., Chen, S., et al. (2018) Flow-cytometric vs. morphologic assessment of remission in childhood acute lymphoblastic leukemia: a report from the Children’s Oncology Group. Leukemia, 32(6): 1370-1379.
Radu, LE., Colita, A., Pasca, S., Tomuleasa, C., Popa, C., Serban, C., et al. (2020) Day 15 and day 33 minimal residual disease assessment for acute lymphoblastic leukemia patients treated according to the BFM ALL IC 2009 protocol: single-center experience of 133 cases. Front Oncol, 10: 923.
Bowman, WP., Larsen, EL., Devidas, M., Linda, SB., Blach, L., Carroll, AJ., et al. (2011) Augmented therapy improves outcome for pediatric high risk acute lymphocytic leukemia: results of Children’s Oncology Group trial P9906. Pediatr Blood Cancer, 57(4): 569-577.
Campana, D., Pui, CH. (2017) Minimal residual disease-guided therapy in childhood acute lymphoblastic leukemia. Blood, 129(14): 1913-1918.
van der Velden, VH., Corral, L., Valsecchi, MG., Jansen, MW., De Lorenzo, P., Cazzaniga, G., et al. (2009) Prognostic significance of minimal residual disease in infants with acute lymphoblastic leukemia treated within the Interfant-99 protocol. Leukemia, 23(6): 1073-1079.
Stutterheim, J., van der Sluis, IM., de Lorenzo, P., Alten, J., Ancliffe, P., Attarbaschi, A., et al. (2021) Clinical implications of minimal residual disease detection in infants with KMT2A-rearranged acute lymphoblastic leukemia treated on the Interfant-06 protocol. J Clin Oncol, 39(6): 652-662.
Goldstone, AH., Richards, SM., Lazarus, HM., Tallman, MS., Buck, G., Fielding, AK., et al. (2008) In adults with standard-risk acute lymphoblastic leukemia, the greatest benefit is achieved from a matched sibling allogeneic transplantation in first complete remission: final results of the international ALL trial (MRC UKALL XII/ECOG E2993). Blood, 111(4): 1827-1833.
Patel, B., Kirkwood, AA., Dey, A., Marks, DI., McMillan, AK., Menne, TF., et al. (2017) Pegylated-asparaginase during induction therapy for adult acute lymphoblastic leukaemia: toxicity data from the UKALL14 trial. Leukemia, 31(1): 58-64.
Larsen, EC., Devidas, M., Chen, S., Salzer, WL., Raetz, EA., Loh, ML., et al. (2016) Dexamethasone and high-dose methotrexate improve outcome for children and young adults with high-risk B-acute lymphoblastic leukemia: a report from Children’s Oncology Group study AALL0232. J Clin Oncol, 34(20): 2380-2388.





