
Cytosponge and Methylation-Based Markers for Detection of Dysplasia in Patients with Barrett's Oesophagus: A Review
DOI:
https://doi.org/10.5281/zenodo.22179542Keywords:
Barrett's Oesophagus, Cytosponge, DNA Methylation, Trefoil Factor 3, Non-Endoscopic ScreeningAbstract
Barrett's oesophagus is the only established precursor of oesophageal adenocarcinoma, and most people who have it do not know. Endoscopy finds it reliably and cannot be offered to everyone at risk, which is why swallowable sampling devices paired with a biomarker have been developed. Whether they detect dysplasia, as opposed to detecting the metaplasia itself, is a separate question that the evidence answers less completely. Objectives: To review the published evidence on non-endoscopic cell collection combined with trefoil factor 3 immunocytochemistry or DNA methylation markers in Barrett's oesophagus: reported accuracy, how performance varies with segment length and sampling, what has been shown specifically for dysplasia, and where these tests sit against endoscopy.
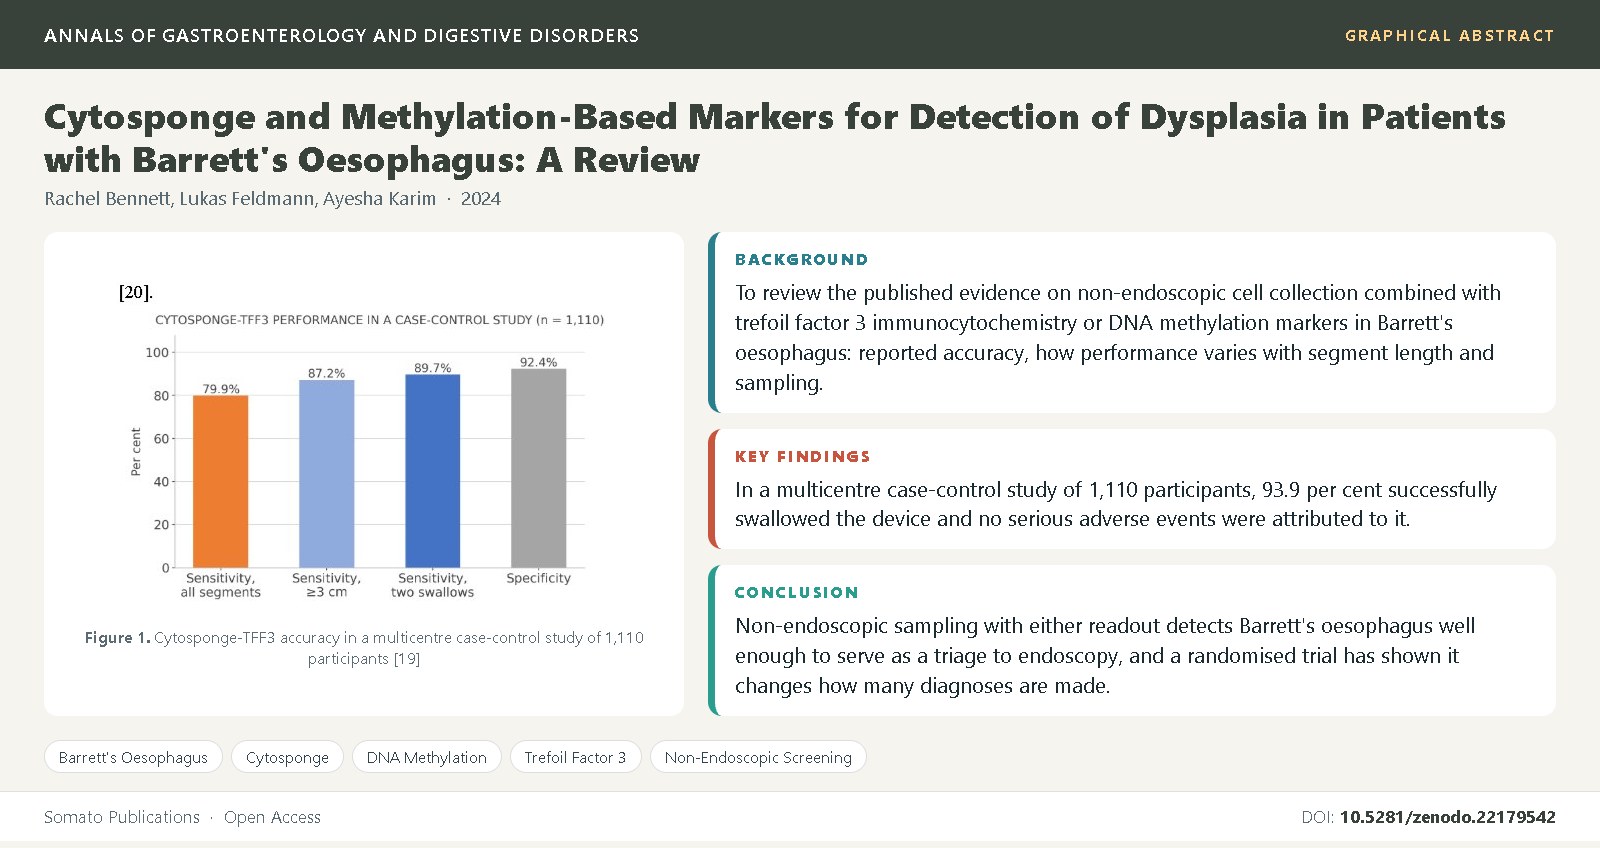
Material and Methods: Narrative review of device development studies, case-control diagnostic studies, randomised trials, cohort studies of risk stratification, cost-effectiveness analyses and guidelines indexed in PubMed and the major gastroenterology journals. Studies were eligible if they reported the accuracy or acceptability of a non-endoscopic sampling device with a biomarker readout, outcomes from its use in a defined population, or guidance on its place in practice. No new patient data were generated; every accuracy estimate quoted is one published by the original investigators. Results: In a multicentre case-control study of 1,110 participants, 93.9 per cent successfully swallowed the device and no serious adverse events were attributed to it. Sensitivity of Cytosponge-TFF3 for Barrett's oesophagus was 79.9 per cent overall, rising to 87.2 per cent for segments of at least 3 centimetres, which carry the higher cancer risk, and to 89.7 per cent when the device was swallowed twice; specificity was 92.4 per cent, and there was no loss of sensitivity in patients with dysplasia. A separate series reported 90.0 per cent sensitivity and 93.5 per cent specificity for circumferential segments of at least 2 centimetres. A balloon-based device paired with methylated vimentin and cyclin A1 achieved sensitivity and specificity both above 90 per cent. In a pragmatic randomised trial across 109 primary care practices, offering the test increased the number of patients diagnosed with Barrett's oesophagus. Conclusion: Non-endoscopic sampling with either readout detects Barrett's oesophagus well enough to serve as a triage to endoscopy, and a randomised trial has shown it changes how many diagnoses are made. The evidence for detecting dysplasia specifically is thinner: sensitivity is reported as preserved in dysplastic patients rather than measured against dysplasia as the primary target, and the biomarker panels that stratify risk within a known Barrett's segment are a different application again. Abbreviations: BE – Barrett's Oesophagus, EAC – Oesophageal Adenocarcinoma, TFF3 – Trefoil Factor 3, VIM – Vimentin, CCNA1 – Cyclin A1, IM – Intestinal Metaplasia, LGD – Low-Grade Dysplasia, HGD – High-Grade Dysplasia, GORD – Gastro-Oesophageal Reflux Disease, EGD – Oesophagogastroduodenoscopy, NGS – Next-Generation Sequencing, FFPE – Formalin-Fixed Paraffin-Embedded, NPV – Negative Predictive Value.
References
Arnold M, Laversanne M, Brown LM, Devesa SS, Bray F. "Predicting the future burden of esophageal cancer by histological subtype: international trends in incidence up to 2030". Am J Gastroenterol 112(2017):1247-1255.
Sung H, Ferlay J, Siegel RL, et al. "Global cancer statistics 2020: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries". CA Cancer J Clin 71(2021):209-249.
Jung KW, et al. "Epidemiology and natural history of intestinal metaplasia of the gastroesophageal junction and Barrett’s esophagus: a population-based study". Am J Gastroenterol 106(2011):1447-1455.
Vaughan TL, Fitzgerald RC. "Precision prevention of oesophageal adenocarcinoma". Nat Rev Gastroenterol Hepatol 12(2015):243-248.
Dulak AM, Stojanov P, Peng S, Lawrence MS, Fox C, et al. "Exome and whole-genome sequencing of esophageal adenocarcinoma identifies recurrent driver events and mutational complexity". Nat Genet 45(2013):478-486.
Shaheen NJ, Falk GW, Iyer PG, et al. "ACG clinical guideline: diagnosis and management of Barrett’s esophagus". Am J Gastroenterol 111(2016):30-50.
Shaheen NJ, Falk GW, Iyer PG, et al. "Diagnosis and management of Barrett’s esophagus: an updated ACG guideline". Am J Gastroenterol 117(2022):559-587.
Banks M, Graham D, Jansen M, et al. "British Society of Gastroenterology guidelines on the diagnosis and management of patients at risk of gastric adenocarcinoma". Gut 68(2019):1545-1575.
Gupta S, Li D, El Serag HB, et al. "AGA clinical practice guidelines on management of gastric intestinal metaplasia". Gastroenterology 158(2020):693-702.
Lao-Sirieix P, Rous B, O’Donovan M, et al. "Non-endoscopic immunocytological screening test for Barrett’s oesophagus". Gut 56(2007):1033-1034.
Lao-Sirieix P, Boussioutas A, Kadri SR, et al. "Non-endoscopic screening biomarkers for Barrett’s oesophagus: from microarray analysis to the clinic". Gut 58(2009):1451-1459.
Maron SB, Chase LM, Lomnicki S, et al. "Circulating tumor DNA sequencing analysis of gastroesophageal adenocarcinoma". Clin Cancer Res 25(2019):7098-7112.
Moinova HR, LaFramboise T, Lutterbaugh JD, et al. "Identifying DNA methylation biomarkers for non-endoscopic detection of Barrett’s esophagus". Sci Transl Med 10(2018):424.
Ococks E, Frankell AM, Masque Soler N, et al. "Longitudinal tracking of 97 esophageal adenocarcinomas using liquid biopsy sampling". Ann Oncol 32(2021):522-532.
Ococks E, Sharma S, Ng AWT, et al. "Serial circulating tumor DNA detection using a personalized, tumor-informed assay in esophageal adenocarcinoma patients following resection". Gastroenterology 161(2021):1705-1708.
Muthusamy VR, et al. "AGA clinical practice update on new technology and innovation for surveillance and screening in Barrett’s esophagus: expert review". Clin Gastroenterol Hepatol (2022).
Kadri SR, Lao-Sirieix P, O’Donovan M, et al. "Acceptability and accuracy of a non-endoscopic screening test for Barrett’s oesophagus in primary care: cohort study". BMJ 341(2010):c4372.
Kadri S, Lao-Sirieix P, Fitzgerald RC. "Developing a nonendoscopic screening test for Barrett’s esophagus". Biomark Med 5(2011):397-404.
Ross-Innes CS, Debiram-Beecham I, O’Donovan M, Walker E, Varghese S, Lao-Sirieix P, et al. "Evaluation of a minimally invasive cell sampling device coupled with assessment of trefoil factor 3 expression for diagnosing Barrett’s esophagus: a multi-center case-control study". PLoS Med 12(2015):e1001780.
Paterson AL, et al. "Role of TFF3 as an adjunct in the diagnosis of Barrett’s esophagus using a minimally invasive esophageal sampling device: the Cytosponge". Diagn Cytopathol (2020). doi: 10.1002/dc.24354.
Berman AG, Tan WK, et al. "Quantification of TFF3 expression from a non-endoscopic device predicts clinically relevant Barrett’s oesophagus by machine learning". (2023).
Ross-Innes CS, Chettouh H, Achilleos A, et al. "Risk stratification of Barrett’s oesophagus using a non-endoscopic sampling method coupled with a biomarker panel: a cohort study". Lancet Gastroenterol Hepatol 2(2017):23-31.
Fitzgerald RC, di Pietro M, O’Donovan M, Maroni R, Muldrew B, Debiram-Beecham I, et al. "Cytosponge-trefoil factor 3 versus usual care to identify Barrett’s oesophagus in a primary care setting: a multicentre, pragmatic, randomised controlled trial". Lancet 396(2020):333-344.
Chak A, et al. "Multicenter, prospective trial of nonendoscopic biomarker-driven detection of Barrett’s esophagus and esophageal adenocarcinoma". Am J Gastroenterol (2024).
Chen WD, Han ZJ, Skoletsky J, et al. "Detection in fecal DNA of colon cancer-specific methylation of the nonexpressed vimentin gene". J Natl Cancer Inst 97(2005):1124-1132.
Moinova HR, Leidner RS, Ravi L, et al. "Aberrant vimentin methylation is characteristic of upper gastrointestinal pathologies". Cancer Epidemiol Biomarkers Prev 21(2012):594-600.
Offman J, Muldrew B, O’Donovan M, Debiram-Beecham I, Pesola F, et al. "Barrett’s oESophagus trial 3 (BEST3): study protocol for a randomised controlled trial comparing the Cytosponge-TFF3 test with usual care". BMC Cancer 18(2018):784.
Januszewicz W, Tan WK, Lehovsky K, Debiram-Beecham I, Nuckcheddy T, Moist S, et al. "Safety and acceptability of esophageal cytosponge cell collection device in a pooled analysis of data from individual patients". Clin Gastroenterol Hepatol (2019).
Shaheen NJ, Komanduri S, Muthusamy VR, et al. "Acceptability and adequacy of a non-endoscopic cell collection device for diagnosis of Barrett’s esophagus: lessons learned". Dig Dis Sci 67(2022):177-186.
Benaglia T, Sharples LD, Fitzgerald RC, et al. "Health benefits and cost effectiveness of endoscopic and nonendoscopic cytosponge screening for Barrett’s esophagus". Gastroenterology 144(2013):62-73.
Heberle CR, Omidvari AH, Ali A, et al. "Cost effectiveness of screening patients with gastroesophageal reflux disease for Barrett’s esophagus with a minimally invasive cell sampling device". Clin Gastroenterol Hepatol 15(2017):1397.





